Introduction
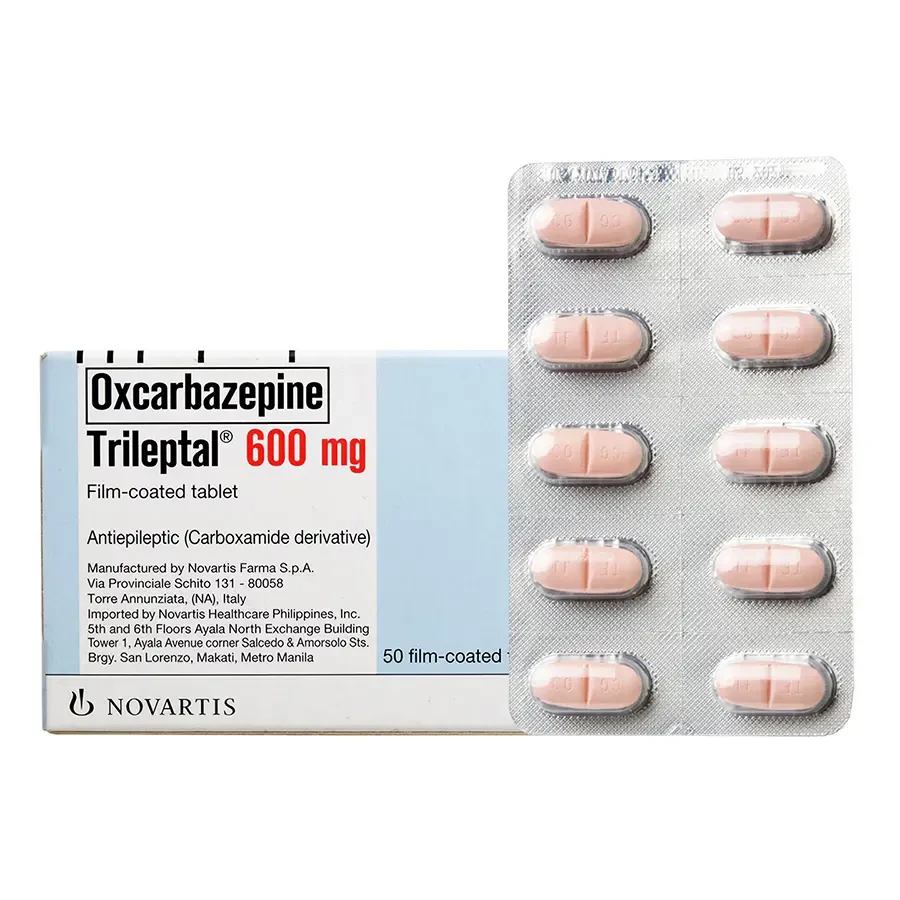
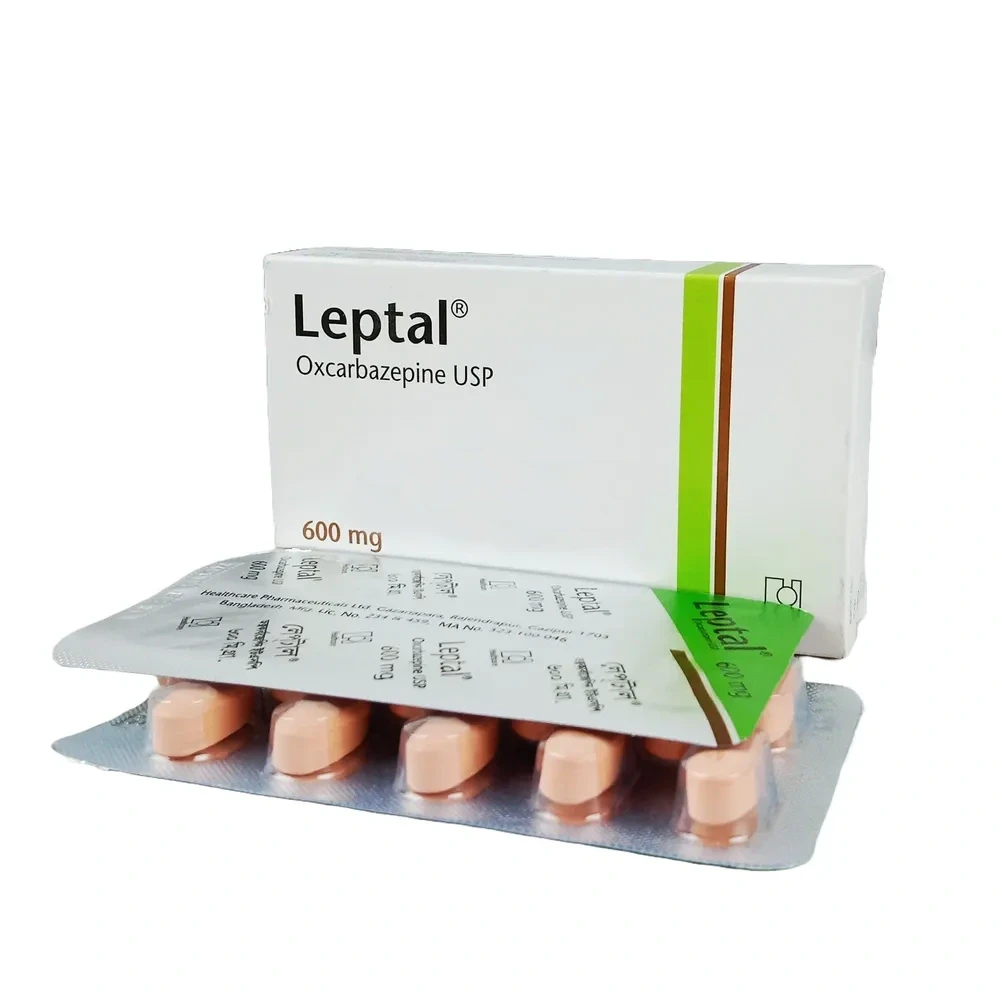
Trileptal Tablet 600 mg is an anti-epileptic medication used in the treatment of partial onset seizures. It is a structural derivative of carbamazepine and exerts a majority of its activity via a pharmacologically active metabolite, MHD, which exists as a racemate in the blood - a pro-drug of the more active (S). Compared to other anti-epileptic drugs, which are generally metabolized via the cytochrome P450 system, oxcarbazepine has a reduced propensity for involvement in drug-drug interactions owing to its primarily reductive metabolism.
Uses
Trileptal Tablet 600 mg is an anti-epileptic used in the treatment of partial-onset seizures.
In the United States, oxcarbazepine is indicated as monotherapy in the treatment of partial-onset seizures in patients 4 years of age and older, and as adjunctive therapy in the treatment of partial-onset seizures in patients 2 years of age and older. In Canada, oxcarbazepine is indicated for use as monotherapy or adjunctive therapy in the treatment of partial-onset seizures in patients 6 years of age and older.
Associated Conditions
Pharmacodynamics
Trileptal Tablet 600 mg is an anticonvulsant drug that reduces the incidence of seizures in epilepsy by inhibiting abnormal electrical activity in the brain.
There have been rare reports of oxcarbazepine resulting in the development of hematologic abnormalities, including agranulocytosis and aplastic anemia. Patients should be undergo frequent laboratory testing and should be monitored closely for signs and symptoms of blood dyscrasias. Trileptal Tablet 600 mg has also been associated with the development of dermatologic reactions which can progress from a simple rash to potentially fatal reactions such as toxic epidermal necrolysis (TEN) or Stevens-Johnson Syndrome (SJS). Patients with the HLA-A3101 and/or HLA-B1502 alleles may be at higher risk of this reaction. Trileptal Tablet 600 mg should be discontinued at the first sign of a drug-induced skin reaction.
Mechanism of Action
The exact mechanism through which oxcarbazepine and its active metaoblite, MHD, exert their anti-epileptic effects is unclear, but is thought to primarily involve the blockade of voltage-gated sodium channels. The opening and closing of sodium channels allows for the propagation of action potentials along neurons - in epilepsy, these action potentials can occur in excess of that required for normal function, and the repetitive and pathological firing of these action potentials leads to seizure activity. Both oxcarbazepine and MHD are thought to inhibit seizure activity by binding to the inactive state of voltage-gated sodium channels, thus prolonging the period in which the receptor is unavailable for action potential propagation. This helps to stabilize hyperexcited neuronal membranes, inhibit repetitive neuron firing, and prevent the spread of seizure activity within the CNS without affecting normal neuronal transmission.
Increased potassium conductance and modulation of voltage-activated calcium channels is also thought to play a role in the anti-seizure activity of oxcarbazepine. Inhibition of glutamatergic activity was thought to contribute to oxcarbazepine's activity, but this effect could not be replicated in vivo.
Absorption
Trileptal Tablet 600 mg is completely absorbed following oral administration. A single 600mg dose of oxcarbazepine resulted in an MHD Cmax of 34 μmol/L and a median Tmax of 4.5 hours. When administered twice daily, steady-state levels of MHD are attained within 2-3 days. The rate and extent of absorption of oxcarbazepine is not affected by food intake.
Volume of Distribution
The apparent volume of distribution of oxcarbazepine is 49 L. The apparent volumes of distribution of (S)- and (R)-MHD were found to be 23.6 L and 31.7 L, respectively.
Protein Binding
The pharmacologically active metabolite of oxcarbazepine, MHD, is approximately 40% bound to plasma proteins, predominantly albumin.
Route of Elimination
Following oral administration, more than 95% of the administered dose of oxcarbazepine is found in the urine. Of this, approximately 49% is MHD glucuronide metabolites, 27% is unchanged MHD, 3% is inactive DHD metabolites, 13% is conjugated oxcarbazepine, and less than 1% is unchanged parent drug. Fecal elimination accounts for only 4% of the administered dose.
Half Life
The plasma half-life of oxcarbazepine is approximately 2 hours and the plasma half-life of MHD is approximately 9 hours.
Clearance
Plasma clearance of oxcarbazepine has been estimated to be approximately 84.9 L/h, whereas plasma clearance of its active metabolite, MHD, was estimated to be 2.0 L/h. Rapid metabolic clearance appears to be the main pathway for oxcarbazepine, while clearance of its metabolites occurs mainly via renal excretion.
Toxicity
The oral LD50 of oxcarbazepine in mammals is 1240 mg/kg and the oral TDLo in children has been reported to be 73 mg/kg. Isolated cases of oxcarbazepine overdose have been reported - patients who ingested up to 24,000mg recovered with symptomatic treatment. Symptoms may include respiratory and CNS depression, movement-related disorders (e.g. dyskinesia, ataxia), nausea/vomiting, hyponatremia, or QTc prolongation. There is no antidote for oxcarbazepine overdose - management should consist of supportive and symptomatic treatment, and consideration should be given to the use of gastric lavage or activated charcoal.
Food Interactions
- Avoid alcohol. Trileptal Tablet 600 mg has CNS depressant properties that may be potentiated by co-administration with alcohol.
- Take with or without food. Co-administration with food does not significantly affect absorption.
Dosage
- Adjunctive Therapy: Maximum increment of 600 mg/day at approximately weekly intervals. The recommended daily dose is 1200 mg/day
- Conversion to Monotherapy: withdrawal concomitant over 3 to 6 weeks;reach maximum dose of Trileptal Tablet 600 mg in 2 to 4 weeks with increments of 600 mg/day at weekly intervals to a recommended daily dose of 2400 mg/day
- Initiation of Monotherapy: Increments of 300 mg/day every third day to a dose of 1200 mg/day.
- Creatinine Clearance <30 mL/min: Initiate at one half the usual starting dose and increase slowly
- Adjunctive Patients (Aged 2–16 Years): For patients aged 4 to 16 years, target maintenance dose should be achieved over 2 weeks. For patients aged 2 to <4 years, maximum maintenance dose should be achieved over 2 to 4 weeks and should not to exceed 60 mg/kg/day
- Conversion to Monotherapy for Patients (Aged 4-16 Years): Maximum increment of 10 mg/kg/day at weekly intervals, concomitant antiepileptic drugs can be completely withdrawn over 3 to 6 weeks
- Initiation of Monotherapy for Patients (Aged 4–16 Years): Increments of 5 mg/kg/day every third day