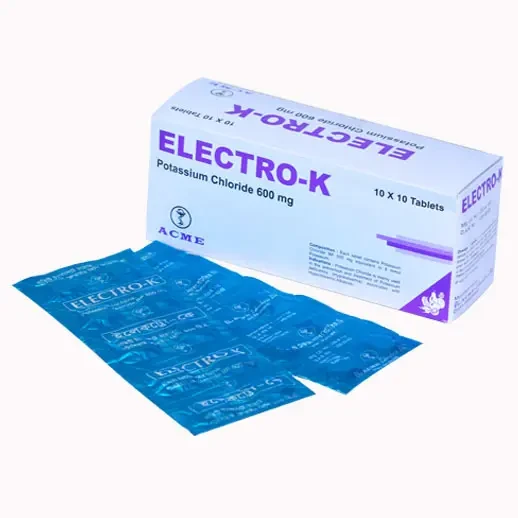
Introduction
A white crystal or crystalline powder used as an electrolyte replenisher, in the treatment of hypokalemia, in buffer solutions, and in fertilizers and explosives.
Uses
Potassium chloride is a potassium salt used to treat hypokalemia.
For use as an electrolyte replenisher and in the treatment of hypokalemia.
Associated Conditions
Pharmacodynamics
The potassium ion is in the principle intracellular cation of most body tissues. Potassium ions participate in a number of essential physiological processes including the maintenance of intracellular tonicity, the transmission of nerve impulses, the contraction of cardiac, skeletal and smooth muscle, and the maintenance of normal renal function. The intracellular concentration of potassium is approximately 150 to 160 mEq per liter. The normal adult plasma concentration is 3.5 to 5 mEq per liter. An active ion transport system maintains this gradient across the plasma membrane. Potassium is a normal dietary constituent and under steady-state conditions the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine. The usual dietary intake of potassium is 50 to 100 mEq per day. Potassium depletion will occur whenever the rate of potassium loss through renal excretion and/or loss from the gastrointestinal tract exceeds the rate of potassium intake. Such depletion usually develops as a consequence of therapy with diuretics, primarily or secondary hyperaldosteronism, diabetic ketoacidosis, or inadequate replacement of potassium in patients on prolonged parenteral nutrition. Depletion can develop rapidly with severe diarrhea, especially if associated with vomiting. Potassium depletion due to these causes is usually accompanied by concomitant loss of chloride and is manifested by hypokalemia and metabolic alkalosis. Potassium depletion may produce weakness, fatigue, disturbances of cardiac rhythm (primarily ectopic beats), prominent U-waves in the electrocardiogram, and, in advanced cases, flaccid paralysis and/or impaired ability to concentrate urine. If potassium depletion associated with metabolic alkalosis cannot be managed by correcting the fundamental cause of the deficiency, e.g., where the patient requires long-term diuretic therapy, supplemental potassium in the form of high potassium food or potassium chloride may be able to restore normal potassium levels. In rare circumstances (e.g., patients with renal tubular acidosis) potassium depletion may be associated with metabolic acidosis and hyperchloremia. In such patients, potassium replacement should be accomplished with potassium salts other than the chloride, such as potassium bicarbonate, potassium citrate, potassium acetate, or potassium gluconate.
Mechanism of Action
Supplemental potassium in the form of high potassium food or potassium chloride may be able to restore normal potassium levels.
Absorption
Potassium is a normal dietary constituent and under steady-state conditions the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine.
Route of Elimination
Potassium is a normal dietary constituent and, under steady-state conditions, the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine. Potassium depletion will occur whenever the rate of potassium loss through renal excretion and/or loss from the gastrointestinal tract exceeds the rate of potassium intake.
Toxicity
The administration of oral potassium salts to persons with normal excretory mechanisms for potassium rarely causes serious hyperkalemia. However, if excretory mechanisms are impaired, of if potassium is administered too rapidly intravenously, potentially fatal hyperkalemia can result. It is important to recognize that hyperkalemia is usually asymptomatic and may be manifested only by an increased serum potassium concentration (6.5-8.0 mEq/L) and characteristic electrocardiographic changes (peaking of T-waves, loss of P-wave, depression of S-T segment, and prolongation of the QT interval). Late manifestations include muscle paralysis and cardiovascular collapse from cardiac arrest (9-12 mEq/L).
Food Interactions
- Take with a full glass of water.
- Take with food. This reduces gastrointestinal irritation.
Dosage
Parenteral dose: Intravenous administration may be required in acute hypokalaemia. One ampoule (10 mL) i.e. 1.5 gm (20 mmol k+) may be added to 500 mL of sodium chloride or glucose intravenous infusion and given slowly over 2 to 3 hours with specialist advice and ECG monitoring in difficult cases. Repeated measurements of potassium are necessary to determine whether further infusions are required and to avoid the development of hyperkalaemia. This is especially liable to occur in renal impairment.